

Clinically reviewed by Dr. Ponlawat Pitsuwan, Physician, Doctor Bangkok.
Last reviewed: November 2026
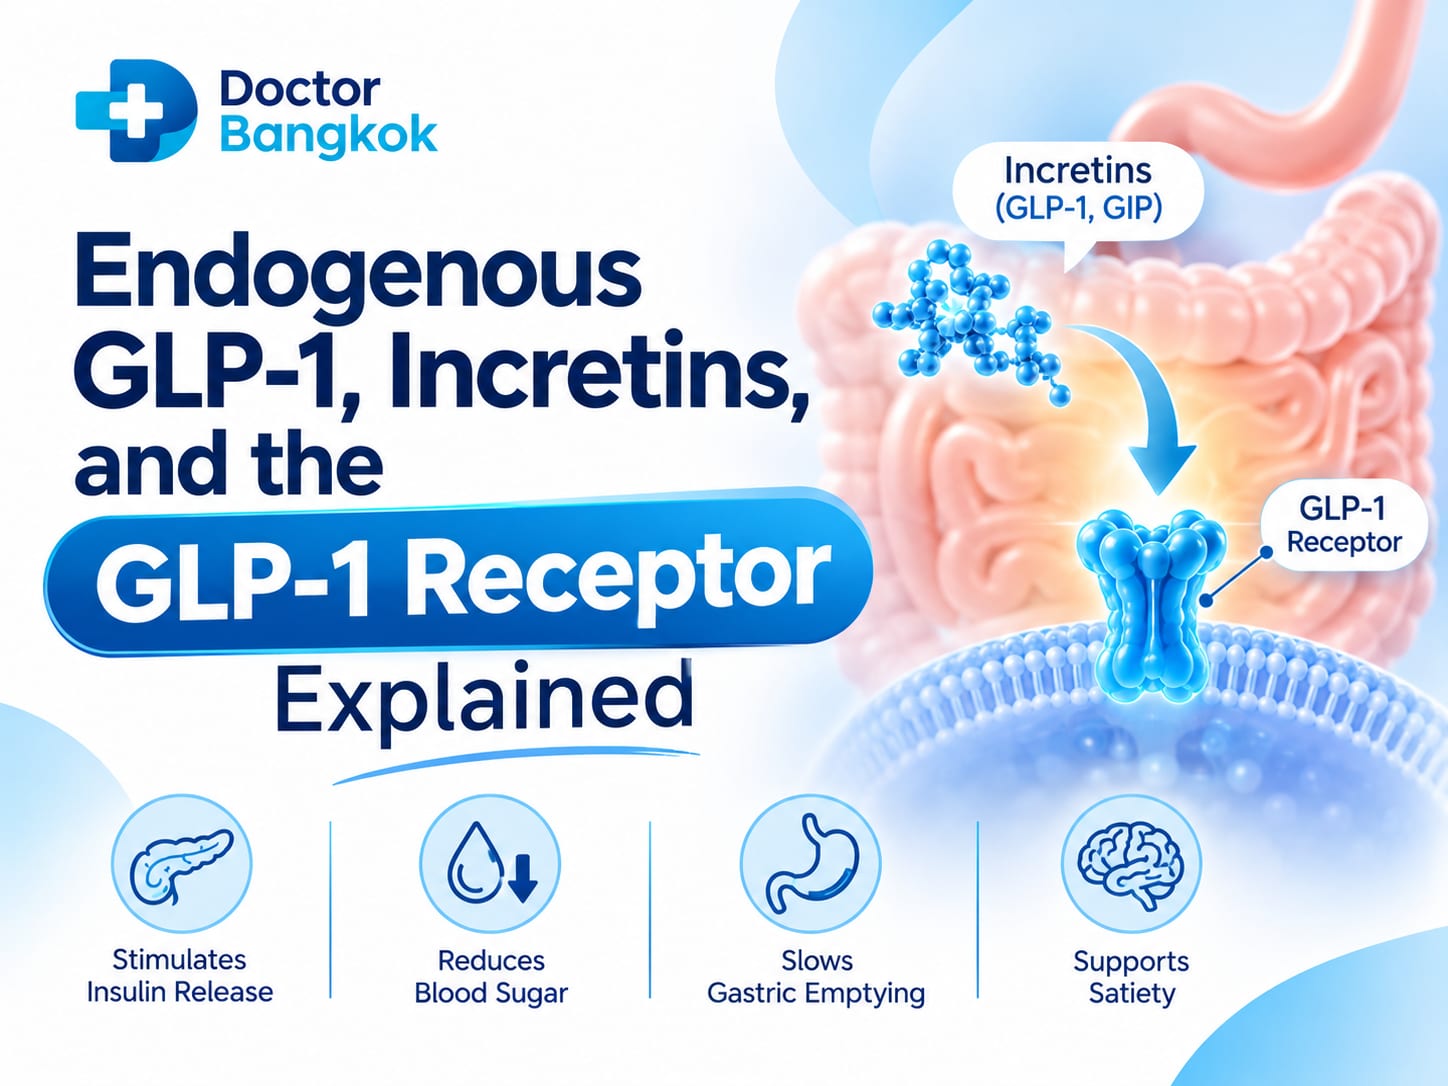
Endogenous GLP-1 is a hormone your gut releases after you eat. It tells your pancreas to produce insulin, slows digestion, and signals your brain that you are full. The problem is it disappears from your bloodstream in under two minutes. GLP-1 medications work by mimicking this signal but lasting far longer, which is a fundamentally different thing from simply topping up what your body already makes.
Your doctor just mentioned incretins, or you are weighing up semaglutide and want to understand what your body does before any drug gets involved. That is the right question. What happens in your gut after a meal, why that signal fades almost instantly, and why medications behave so differently from your own biology are the things worth understanding first.
This page covers the science in plain terms. If you are sitting in a clinic in Bangkok working out your options, knowing this foundation makes every conversation with your doctor sharper.

Where Natural GLP-1 Comes From
GLP-1 is made by L-cells, a type of cell scattered through the lining of your small and large intestine. They sit in direct contact with whatever you just ate.
When nutrients arrive, L-cells release GLP-1 into the bloodstream. They do this by processing a larger protein called proglucagon and cutting it into active fragments. The same gene is active in your pancreas and brainstem, but those tissues cut it differently and produce other hormones.
GLP-1 also slows gastric emptying, meaning it slows how fast food leaves your stomach. That is part of why you feel full after eating. Food arrives, GLP-1 is released, digestion slows, insulin rises, and appetite dips.
What Triggers GLP-1 Release After a Meal
Not all foods trigger the same response. Carbohydrates and fats are the strongest stimulants. Protein produces a weaker and slower response.
In Bangkok, a typical meal is high in refined carbohydrates: white rice, rice noodles, sweetened drinks. These meals do trigger GLP-1 release, but the hormone is gone within minutes. The signal is real but too brief to produce lasting appetite suppression on its own.
A meal higher in fibre and protein produces a more sustained incretin response. This is one reason dietary composition matters even when you are thinking about medication. The page on whether you can boost GLP-1 naturally covers dietary and lifestyle factors in more detail.
GIP and the Broader Incretin System
GLP-1 does not work alone. GIP, or glucose-dependent insulinotropic polypeptide, is the other main incretin hormone. It is released from K-cells in the upper small intestine, mostly in response to fat and carbohydrates.
Both GIP and GLP-1 amplify insulin release after a meal. Eating glucose by mouth produces far more insulin than giving it directly into a vein, and incretins account for a substantial part of this difference, estimated at roughly half of the insulin released after a meal in studies of healthy adults.
GIP matters more now than it did a few years ago. Tirzepatide, sold as Mounjaro, targets both the GIP and GLP-1 receptors at the same time. Understanding that it works on two incretin pathways helps explain why its effects on weight can differ from a GLP-1-only drug.
Where the GLP-1 Receptor Is Found
The GLP-1 receptor sits on beta cells in the pancreas, which are the cells that produce insulin. When GLP-1 binds to it, insulin secretion increases, but only when blood glucose is already elevated. This glucose-dependent mechanism means GLP-1 rarely causes dangerous low blood sugar on its own.
The receptor is also expressed in the heart, kidneys, and brain. In the hypothalamus, GLP-1 receptors contribute to the feeling of being full. In the brainstem, specifically an area called the nucleus tractus solitarius, signals arrive from both the gut via the vagus nerve and from circulating GLP-1.
The brainstem also produces its own GLP-1 through neurons that project into appetite-regulating areas. This is separate from the gut-derived GLP-1 released after a meal. It helps explain why GLP-1 drugs can affect appetite through brain pathways that your own hormone barely reaches.
Why Natural GLP-1 Lasts Only Minutes
Active GLP-1 has a half-life of roughly one to two minutes in the bloodstream. Most of it is gone before it reaches the pancreas in significant amounts. The rest is cleared by the kidneys.
This is not a design flaw. It is a tightly controlled system where the signal is meant to be brief.
How the Breakdown Enzyme Works
The enzyme responsible for most of this rapid breakdown is DPP-4, or dipeptidyl peptidase-4. It cleaves GLP-1 near the start of the molecule, producing an inactive fragment that cannot bind the GLP-1 receptor. The kidneys then clear what remains.
DPP-4 inhibitors, sometimes called gliptins, block this enzyme. That slows GLP-1 breakdown modestly. The effect on blood sugar exists but is weaker than a GLP-1 receptor agonist, because you are still working with the small amounts your body produces rather than activating the receptor directly.
How Medicines Copy and Extend This Signal
GLP-1 receptor agonists like semaglutide are not natural GLP-1. They are engineered molecules designed to bind the same receptor but resist DPP-4 cleavage. Semaglutide has a half-life of approximately one week and reaches receptor concentrations that endogenous GLP-1 never achieves.
Taking semaglutide is not topping up what your body makes. It activates the GLP-1 receptor at levels far above anything your own system produces, and does so continuously. The cardiovascular benefits, kidney-protective signals, and appetite suppression seen in major trials occur at these pharmacological levels, not at the levels your body generates after a meal.
GLP-1 receptor activation also reduces glucagon release from the pancreas, which lowers glucose production by the liver. Your own GLP-1 does this briefly after every meal. A receptor agonist does it around the clock.
At Doctor Bangkok, before anyone starts a GLP-1 programme, a physician reviews your fasting insulin, C-peptide, and postprandial glucose alongside your cardiovascular risk. You can check your baseline numbers with the BMI Calculator Bangkok or the Cardiovascular Risk Calculator Bangkok before your appointment. The weight-loss injections page covers the treatment options available at the clinic, including both semaglutide and tirzepatide.
Thinking about starting a GLP-1 medication in Bangkok? Doctor Bangkok offers same-day consultations at our clinic on Sukhumvit Soi 13, open 24 hours. A physician will review your metabolic health, explain your options including semaglutide and tirzepatide, and build a treatment plan specific to you. If you prefer, our doctor-on-call service can come to your hotel or condo anywhere in Bangkok within one hour. Contact us to book.
Frequently Asked Questions
Dr. Ponlawat Pitsuwan
Physician, Doctor Bangkok
a private medical clinic in central Bangkok, open 24/7, with a doctor-on-call service that comes to your hotel or condo within one hour. He sees expats, residents, and medical tourists for metabolic health assessments, GLP-1 therapy consultations, and general medical care. His focus is straightforward, evidence-based care delivered in plain language.
References
- Baggio LL, Drucker DJ. Biology of incretins: GLP-1 and GIP. Gastroenterology, 2007;132(6):2131-2157.
- Nauck MA, Meier JJ. Incretin hormones: Their role in health and disease. Diabetes, Obesity and Metabolism, 2018;20 Suppl 1:5-21.
- Drucker DJ. The biology of incretin hormones. Cell Metabolism, 2006;3(3):153-165.
- Lincoff AM, et al. Semaglutide and Cardiovascular Outcomes in Obesity without Diabetes (SELECT trial). New England Journal of Medicine, 2023;389(24):2221-2232.
The information in this article is for educational purposes only and does not constitute medical advice. It should not be used to self-diagnose or replace a consultation with a qualified physician. If you have concerns about your health, contact a licensed medical professional. For appointments at Doctor Bangkok, visit doctorbangkok.co.th.

Dr. Ponlawat Pitsuwan is a physician at Doctor Bangkok, a private clinic in central Bangkok. He sees expats, residents, and medical tourists for general medicine, wellness consultations, and IV therapy. His focus is straightforward, evidence-based care delivered in plain language.

